
 The Standard Group Plc is a multi-media organization with investments in media
platforms spanning newspaper print
operations, television, radio broadcasting, digital and online services. The
Standard Group is recognized as a
leading multi-media house in Kenya with a key influence in matters of national
and international interest.

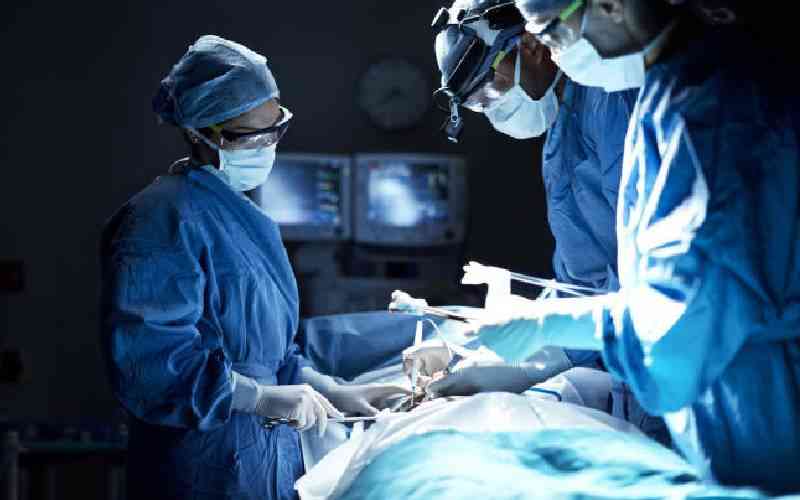
President William Ruto has called African countries to reduce its dependence on imported medicines and strengthen local production, in line with the African Union's ambition to meet 60 per cent of its health-product needs through local manufacturing by 2040.
He said achieving the target will require governments to move beyond political commitments and implement reforms in procurement, regulation, financing, technology transfer and industrial policy.
Ruto said, for decades Africa has carried a big share of the world’s disease burden while relying heavily on medicines, vaccines and medical technologies manufactured elsewhere.
“Africa carries about a quarter of the world's disease burden. We make less than six per cent of our medical supplies. We make about one per cent of the vaccines we use,” Ruto said in remarks delivered by Health Cabinet Secretary Aden Duale.
This emerged at a side event during the 81st United Nations General Assembly in New York, hosted by the Government of Kenya and the Africa Centres for Disease Control and Prevention (Africa CDC).
He noted that the imbalance became painfully visible during COVID-19, when countries across the continent competed for scarce supplies and often found themselves behind wealthier markets in the global queue.
“Africa waited longer, paid more and received less. Our people paid the price for a supply chain we did not own. We will not go through that again,” Ruto said.
Speaking in his capacity as African Union champion for local manufacturing of health products, Ruto said the African Union has now placed local manufacturing at the centre of its health-security agenda.
Perhaps the clearest example of what this new model could look like is emerging around alimatravir, an investigational once-monthly oral HIV-prevention medicine developed by MSD and currently in Phase 3 clinical trials.
He revealed that Kenya is preparing to manufacture Alimatravir, an investigational once-monthly oral HIV-prevention medicine, while also calling for harmonised regulation, pooled procurement, long-term financing, technology transfer and coherent national policies.
“We are building domestic manufacturing capacity, and the skills, regulation and markets that keep factories alive. But no single African country can do this alone,” he said.
In July 2026, MSD announced voluntary licensing arrangements with seven generic manufacturers, including three African companies: Universal Corporation Limited in Kenya, Quality Chemical Industries Limited in Uganda and Aspen Pharmacare in South Africa.
The licences cover potential supply to 129 low- and lower-middle-income countries, subject to successful development and regulatory approval.
UNAIDS has welcomed the early manufacturing strategy, noting that preparations for financing, demand forecasting, accessibility and regulatory readiness could help shorten the time between approval and patient access.
“For the first time, African manufacturers are part of the licensing for an HIV medicine from the very start. The science is happening here too,” Ruto said.
Dr. Priya Agrawal, Vice President of Health Equity and Partnerships at MSD called for stronger African pharmaceutical manufacturing capacity to ensure rapid, equitable and sustainable access to alimatravirs.
“If the trials are successful, we want to ensure rapid access, we don't want to wait years, broad access, for everyone that needs it, and sustainable access, which means the local manufacturers actually have to make some money,” she said.
She said MSD had deliberately chosen three African manufacturers in countries hosting clinical trials, including Universal Corporation in Kenya, Quality Chemical Industries in Uganda and Aspen Pharmacare in South Africa.
She stressed that African manufacturers must receive the capabilities, financing and market support needed to compete on cost, quality and reliability.
“This is about strengthening African research and manufacturing, supporting skilled jobs and local private businesses, expanding regional trade and the journey from innovation to impact,” she said.
Africa CDC's African Pooled Procurement Mechanism is designed to aggregate demand across countries, strengthen bargaining power and create more predictable markets for manufacturers. Africa CDC
“A manufacturer should not face a different process in every African country. We must speed up harmonisation and give the African Medicines Agency the strength to lead. One continent. One coherent pathway. Faster access for patients,” Ruto said.
The declaration also backed pooled procurement, sustainable financing, skills development and technology transfer. But the challenge is to create an ecosystem in which those factories can survive.
Duale announced that Kenya has made progress in getting WHO certification of kenya pharmacy and poison board to Maturity level 3.
“Africa's health security and sovereignty will depend on building not only manufacturing capacity, but also the markets, financing and regulatory systems needed to make local production sustainable and competitive,” Duale said.
Duale added that development banks, private investors and international partners therefore have a role in creating financing instruments suited to the pharmaceutical industry's long development cycles.
Kenyan senior advisor on global health diplomacy Dr. Nicholas Muraguri said localized pharmaceutical production can strengthen Africa’s health security and accelerate access to new HIV prevention technologies.
He said localised production could help ensure life-saving innovations are delivered swiftly, affordably and reliably across 129 low- and middle-income countries.
“By combining an ultra-low-cost, once-monthly pill with localised African manufacturing, we are equipping communities to protect themselves, secure their own supply chains, and systematically halt new HIV infections,” Muraguri said.
Muraguri said prioritizing manufacturing through strategic regional hubs, initially starting in Kenya with Universal Corporation Limited, could provide a foundation for greater pharmaceutical self-reliance across the continent.
“African manufacturers often operate in fragmented markets, face different regulatory requirements from country to country and struggle to secure the long-term orders and capital required to compete with established producers in India and elsewhere,” he said.
WHO has previously estimated that imports account for roughly 70- 90 percent of medical products consumed in Africa, while the continent produces less than 1 p.c of the vaccines it uses.
According to WHO, Kenya has more than 37 licensed pharmaceutical manufacturers producing hundreds of formulations, yet it still imports an estimated 70-80 percent of the pharmaceuticals it consumes.
Its manufacturers also operate below their potential capacity. Kenya's 2026–2030 Health Products and Technologies Local Manufacturing Strategy therefore seeks to increase utilisation, strengthen regulatory systems and introduce more predictable procurement arrangements.
The solution being advanced by African health leaders rests on five interconnected pillars: predictable markets, harmonised regulation, regional trade, long-term financing, and investment in science and skills.
He noted that governments must actually buy locally manufactured products when those products meet required standards.
The African Medicines Agency is increasingly being positioned as an important part of that architecture.
WHO and AMA have noted that fragmented regulatory systems remain a major obstacle to timely access to quality-assured products.
The African Continental Free Trade Area can potentially turn fragmented national markets into a much larger continental market but only if customs, procurement and regulatory barriers do not prevent medicines from reaching patients.
Pharmaceutical manufacturing requires equipment, quality-control systems, research, skilled personnel, regulatory compliance and working capital require investments that may take years to generate returns.
The fifth pillar is science and skills: scientists, pharmacists, engineers, plant managers, regulators and research institutions capable of developing and manufacturing products on the continent.













 join
